HOME > Weekly Case > Weekly Case
Weekly Case
종결
Case No. 440
2017-04-01~2017-04-30
출제자 : 배윤정
Hit : 430
| Period | 2017-04-01~2017-04-30 |
|---|---|
| Diagnosis | Acute alcoholic demyelination |
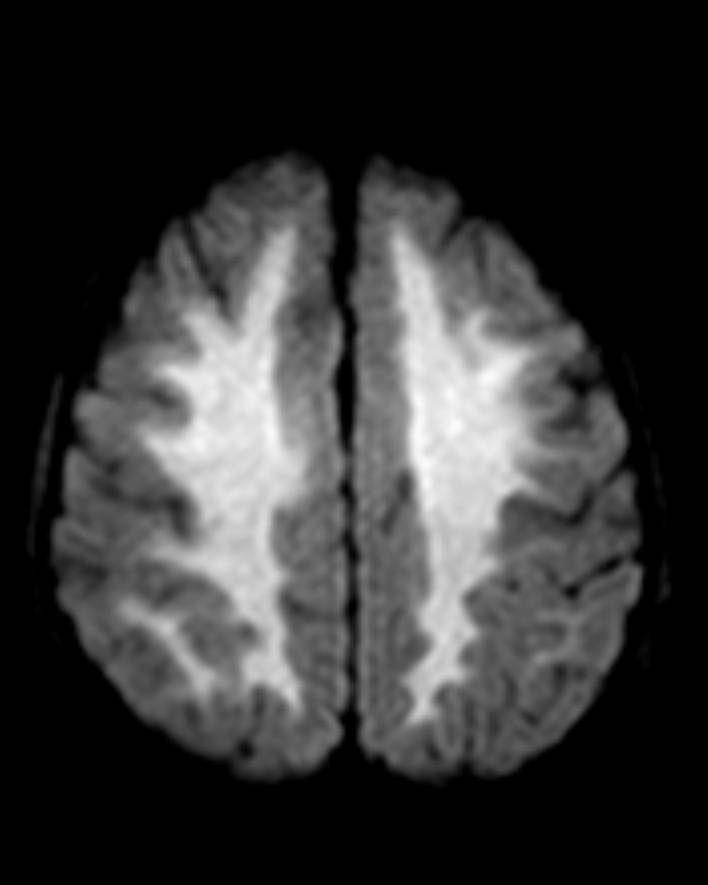
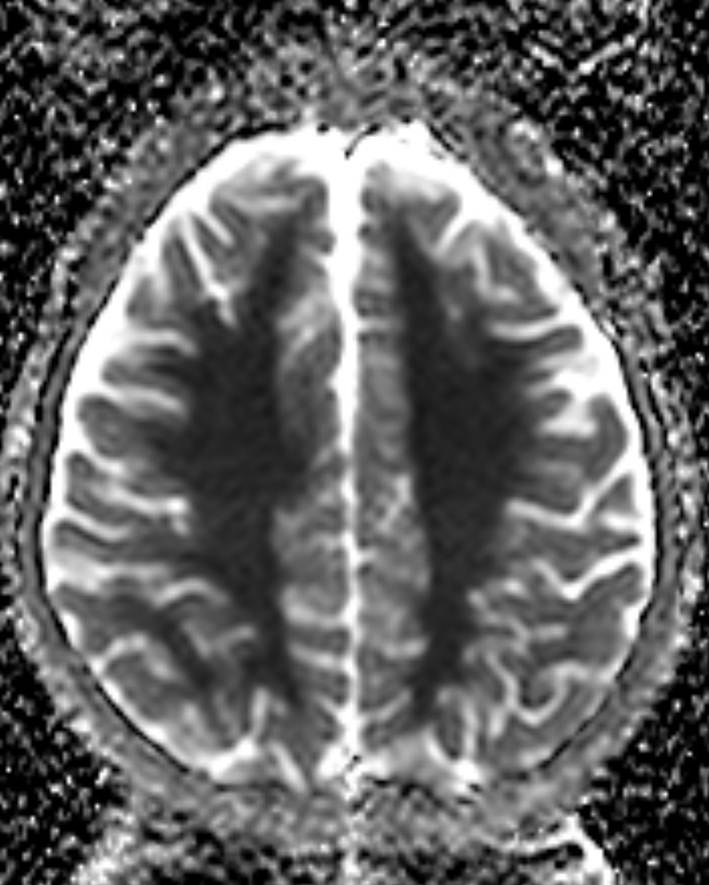
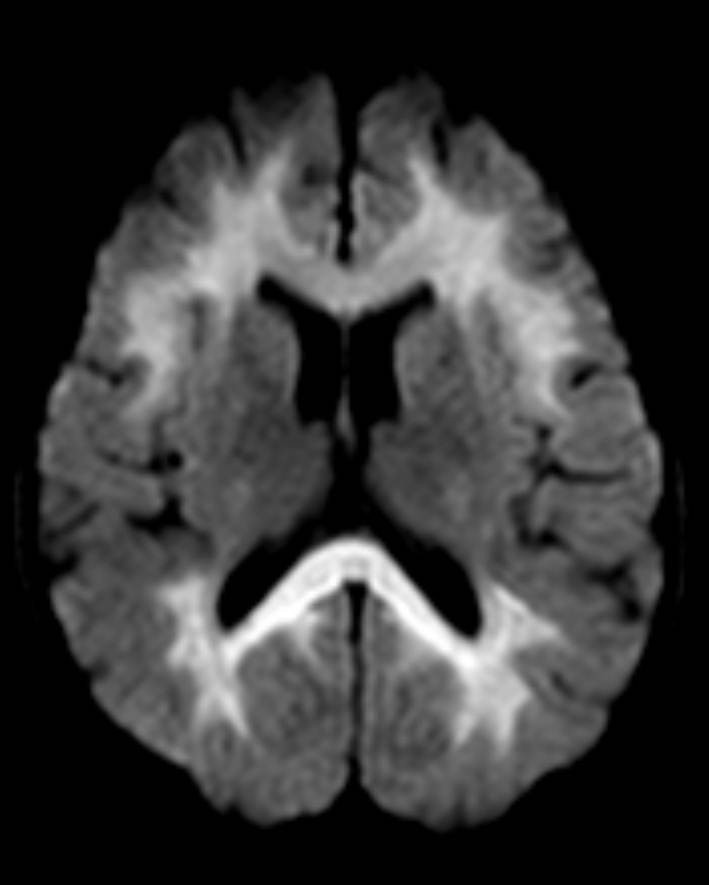
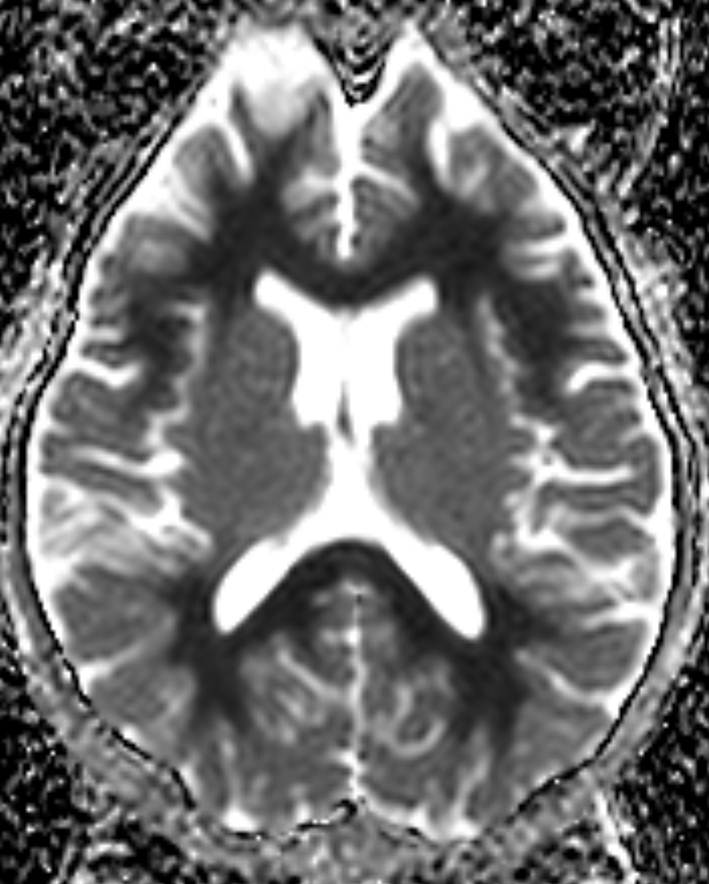
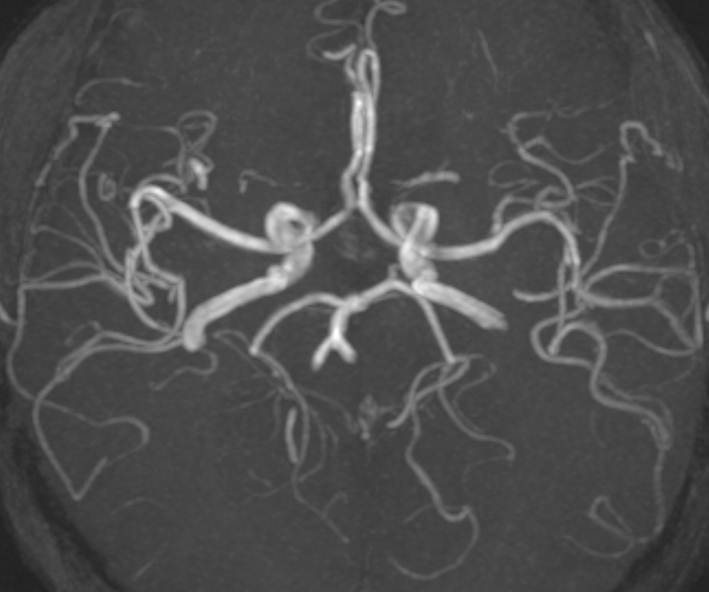
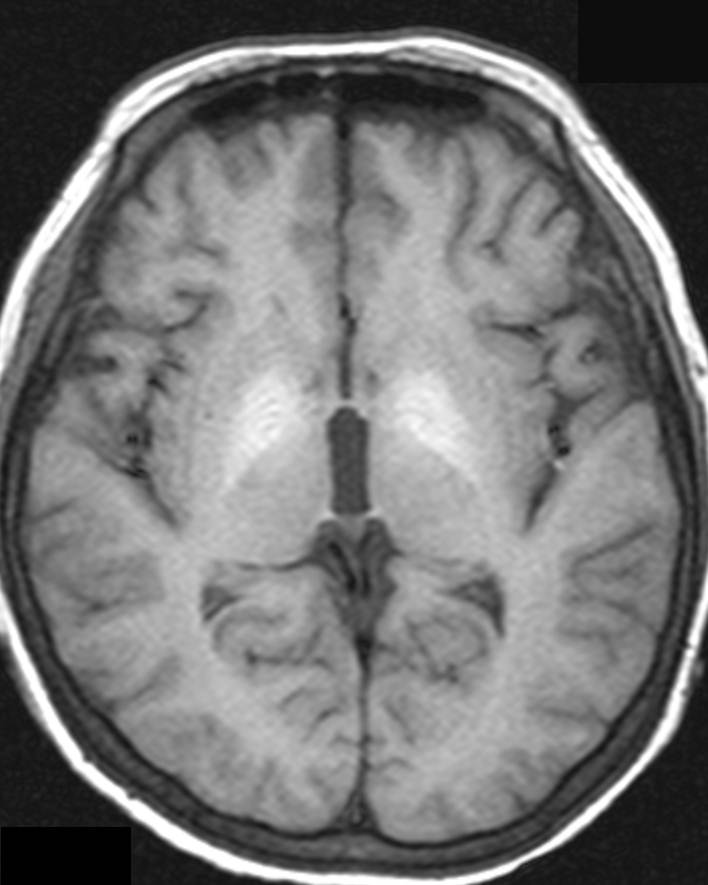
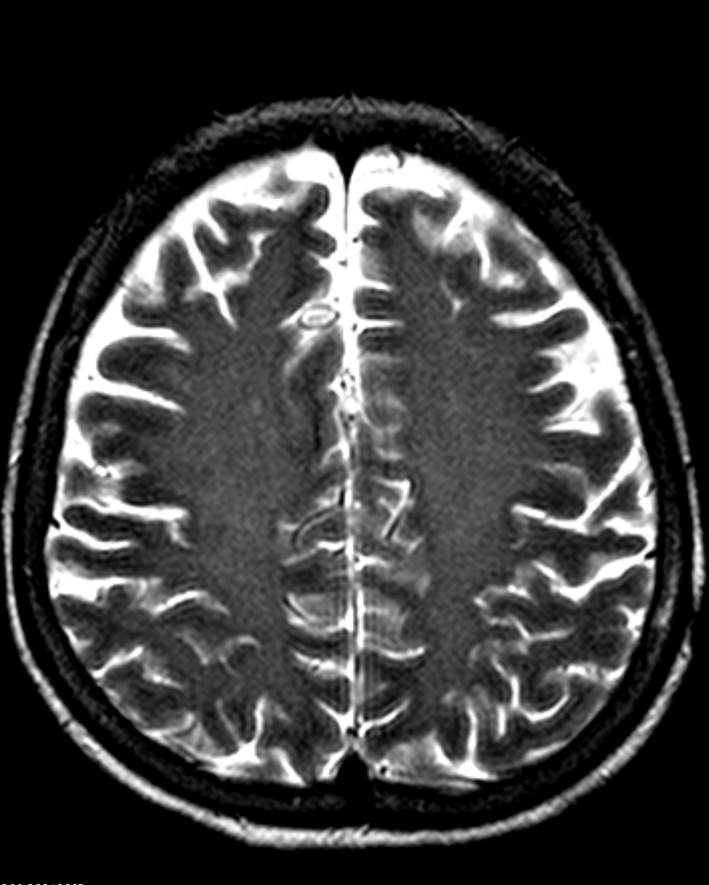
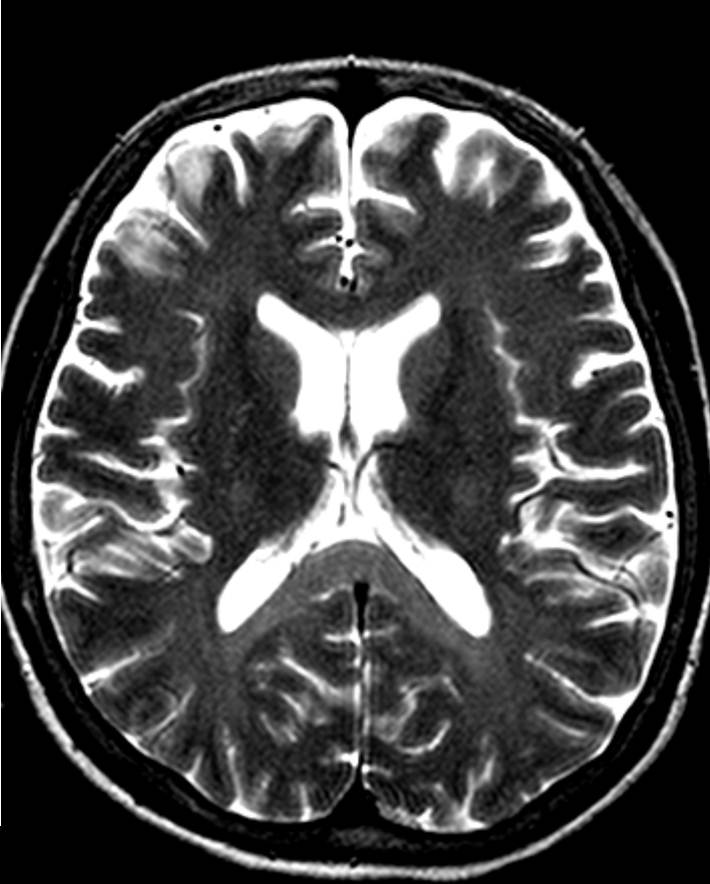
| Clinical information | F/31 History of recurrent acute pancreatitis on chronic pancreatitis Current problem: Drowsy mentality, acute onset GTC-type seizure What is your diagnosis? |
| Discussion | Acute alcoholic demyelination Patient’s history: Chronic heavy alcoholic, Alcoholic LC MRI: -Diffuse white matter T2 hyperintense lesions including corpus callosum with diffusion-restriction -T1 hyperintensity in bilateral globi pallidi, suggesting hepatic dysfunction -Normal MRA Acute alcoholic demyelination = Acute toxic effect from alcohol, acute alcoholic encephalopathy, diffuse alcohol-induced toxic demyelination -Ethanol causes both direct and indirect neurotoxicity by crossing blood-brain barrier. -Increasing risk of stroke and hepatic encephalopathy -MR findings a. Nonspecific multifocal white matter T2 hyperintensities b. Less common: Diffuse white matter T2 hyperintensities from toxic demyelination c. Marchiafava-Bignami disease: T2 hyperintensity in corpus callosum d. Diffuse toxic myelination can be enhanced. e. Chronic stage: cerebral atrophy, especially frontal lobes, and cerebellum, superior vermis -Differential diagnosis for diffuse demyelination Toxic demyelination from chemotherapy/CO poisoning/inhaled heroin, acquired/inherited metabolic disorders -Differential diagnosis for corpus callosal hyperintensity Status epilepticus, drug toxicity, encephalitis, hypoglycemia |
| Correct answer |
Correct Answer
Semi-Correct Answer |